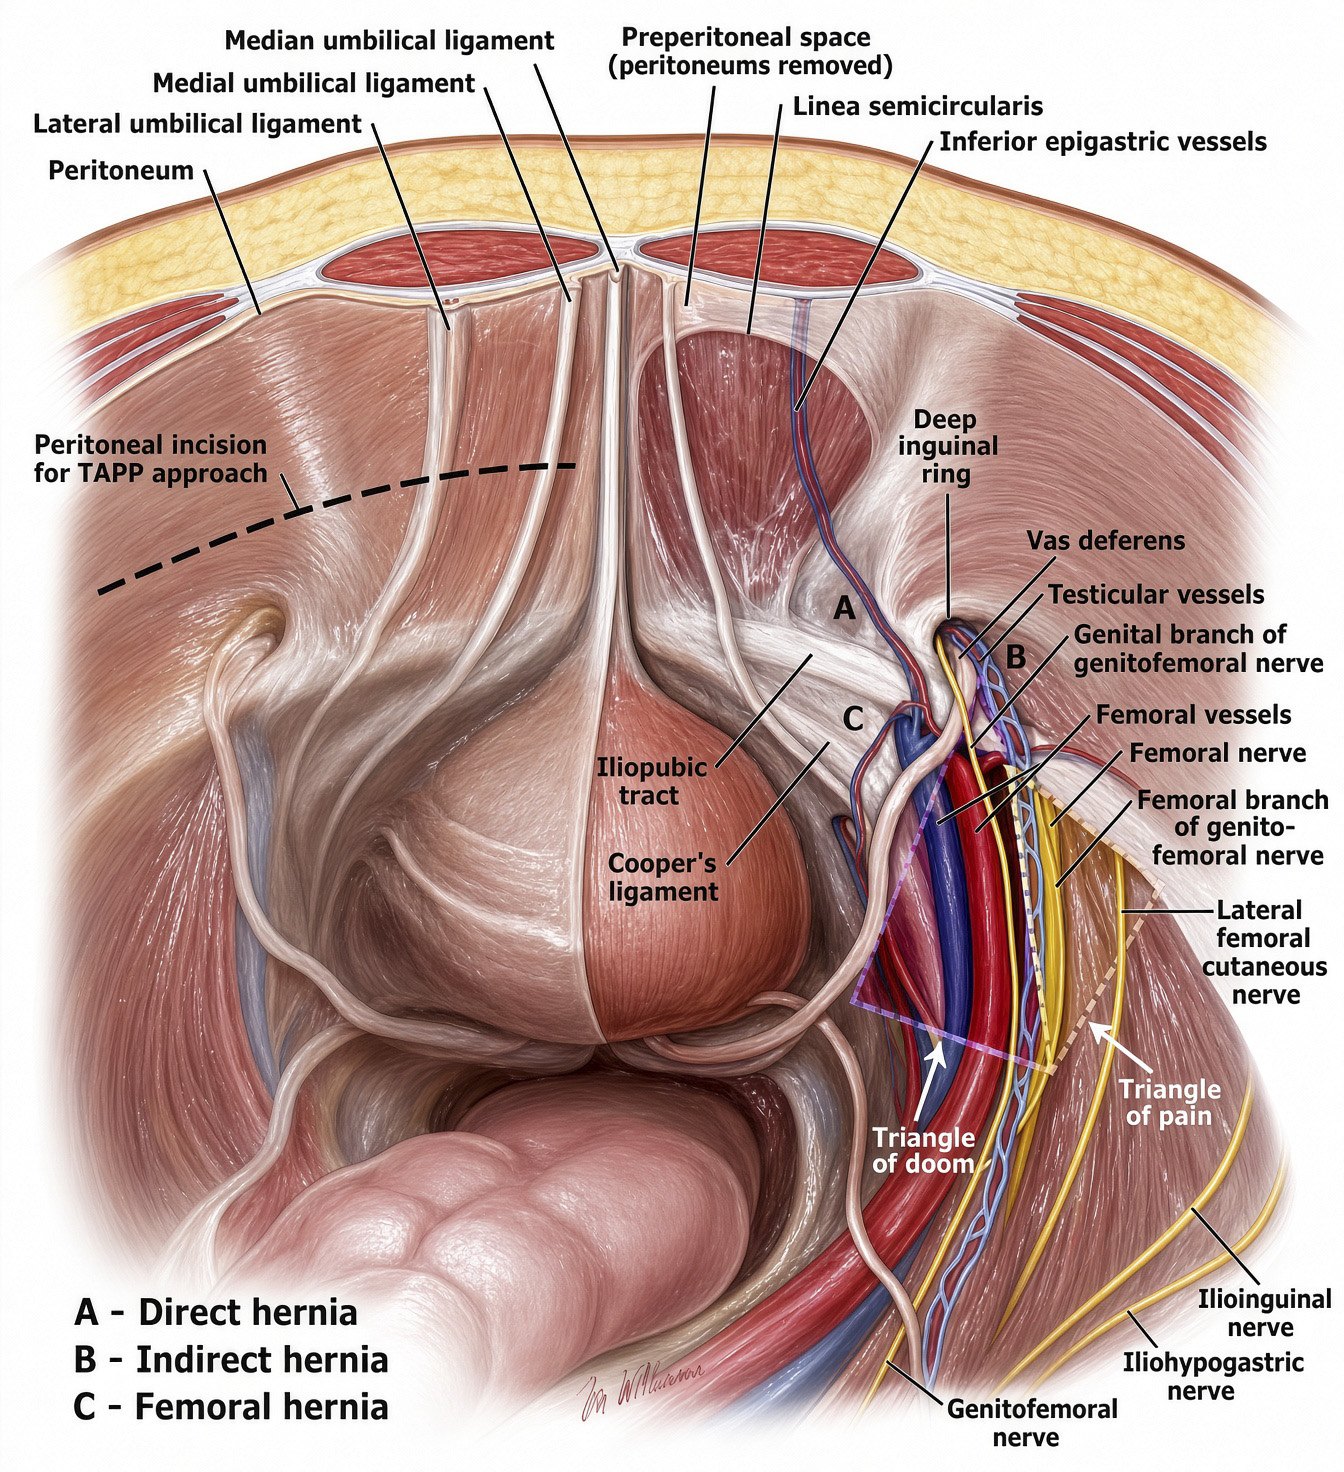
Foley, then Verres or Hasson entry, 30° camera, & triangulate ports on target anatomy.
Inspect for contralateral hernia (should consent for possible bilateral repair).
Take down peritoneum horizontally from midline & extending laterally - ensuring an adequate pocket for mesh placement. This will be closed with absorbable suture at the end of the case.
Dissect preperitoneal space down to expose medial to Cooper's ligament & laterally past all three potential hernia spaces (direct, indirect, and femoral) taking care to preserve the epigastric vessels anteriorly & the iliac neurovasculature, genitofemoral & lateral femoral cutaneous nerves posteriorly.
After reducing the hernia, ensure peritoneum is reflected posteriorly enough to allow for proper mesh placement.
Place a self-fixing polyester mesh covering from pubis to lateral abdominal wall.
Anchor it to the pubic tubercle medially and along the superior edge to the conjoint tendon superiorly, with a keyhole for the spermatic cord. Avoid tacks inferior to the iliopubic tract to avoid the risk of neurovascular injuries in the so-called triangle of doom and triangle of pain.
Educational aid only. Verify every dose, indication, and guideline against current institutional protocol. This is not a substitute for clinical judgment.