
Atlas
Tables and Figures
Every table and figure extracted from the manual, oral-board deck, and trauma/critical-care material, listed alphabetically.
1x
The Concise Surgery Review Manual
| 1x | Hydrocortisone |
|---|---|
| 4x | Prednisone, prednisolone |
| 5x | Methylprednisolone |
| 30x | Dexamethasone |
Acute-care blood-pressure targets
Trauma and Critical Care
| Condition | Target | Preferred IV | Avoid |
|---|---|---|---|
| Aortic dissection | SBP <120 and HR <60 now | Esmolol/labetalol THEN nicardipine/NTP | Vasodilator first |
| ICH | If 150–220, 140 is safe; avoid <130 | Nicardipine, clevidipine, labetalol | NTP, hydralazine swings |
| AIS + lytic | <185/110 before, <180/105 after | Labetalol, nicardipine | Overshoot |
| ACS / flash edema | SBP <140 | NTG, nicardipine | |
| Eclampsia | SBP <160 | Labetalol, hydralazine, nifedipine + Mg | ACEI, NTP |
Anaphylaxis, LAST, MH, NMS, serotonin syndrome
Trauma and Critical Care
| Syndrome | 1st line | 2nd / 3rd | Avoid |
|---|---|---|---|
| Anaphylaxis | Epi 0.3–0.5 mg IM mid-thigh q5 min; then drip 0.05–0.3 mcg/kg/min | Fluids, albuterol, airway. Adjunct H1/H2 + steroid do not replace epi | Epi SQ. Delayed IM while placing a central line |
| LAST | Stop injection. Airway. Benzo for seizure. 20% lipid 1.5 mL/kg bolus, then 0.25 mL/kg/min | Repeat bolus ×1–2. ACLS with low-dose epi (~1 mcg/kg). Bypass if refractory | Vasopressin, CCB, local-anesthetic antiarrhythmics (lidocaine) |
| MH | Call for help. Dantrolene 2.5 mg/kg IV repeat to 10 mg/kg. Stop volatile/succ. 100% O2 high flow | Cool, treat hyperK, bicarb, CRRT if needed. MH hotline 1-800-644-9737 | CCB + dantrolene (hyperK). Recrudescence watch 24–48 h |
| NMS | Stop dopamine blocker. Cool. Benzos. IVF | Bromocriptine 2.5–10 mg q6–8h or amantadine; dantrolene if rigid/hyperthermic | Restarting the antipsychotic early |
| Serotonin syndrome | Stop offenders (SSRI, tramadol, linezolid, fentanyl, MAOI, methylene blue) | Benzos. Cyproheptadine 12 mg then 2 mg q2h (max 32 mg/d) if moderate | Bromocriptine (wrong syndrome). Physical restraint without meds |
Antibiotic duration by setting
Trauma and Critical Care
| Setting | 1st line | Allergy / alt | Duration |
|---|---|---|---|
| CAP ward, no risk factors | β-lactam (amp-sulbactam 3 g q6 / ceftriaxone 1–2 g) + macrolide OR levo 750 / moxi 400 | Levofloxacin monotherapy; doxy + β-lactam | 5 d if clinically better |
| CAP ICU | β-lactam + macrolide OR β-lactam + FQ. Add vanc/linezolid if MRSA risk; add pip-tazo/cefepime/meropenem if Pseudomonas risk | Aztreonam + FQ + MRSA agent if severe PCN allergy | 5–7 d; longer if not improving |
| HAP / VAP low MDR | Pip-tazo 4.5 g q6 (ext inf), cefepime 2 g q8, or meropenem 1 g q8 | Cipro/levo + vanc if needed | 7 d |
| HAP / VAP high MDR / prior IV abx 90 d / septic shock | 2 antipseudomonals of different classes + MRSA coverage pending cultures | Avoid double β-lactam; use AG or FQ as second agent | 7 d if source controlled and improving |
Anticoagulant and antiplatelet reversal
Trauma and Critical Care
| Agent | 1st line | Dose notes | Caveats |
|---|---|---|---|
| Warfarin | 4-factor PCC + vit K 10 mg IV | INR-based PCC (~25–50 U/kg); FFP only if no PCC | Recheck INR 15–30 min |
| Dabigatran | Idarucizumab 5 g IV | If unavailable: PCC + consider HD | Time since last dose matters |
| Rivaroxaban / apixaban / edoxaban | Andexanet if available and labeled; else 4F-PCC 50 U/kg (max 2000–2500 U common practice) | ANNEXA-4 vs unapproved PCC — both used | Andexanet complicates subsequent heparin/PCI |
| UFH | Protamine 1 mg per 100 U given in last 2–3 h | Max ~50 mg first dose; slow IV | Anaphylaxis risk, especially NPH / fish |
| LMWH (enoxaparin) | Protamine ~1 mg per 1 mg enox if <8 h (0.5 mg if 8–12 h) | Incomplete reversal | |
| Antiplatelet (ASA/P2Y12) | DDAVP 0.3 mcg/kg; platelets if intracranial or uncontrolled | One apheresis unit | Stent thrombosis risk if you blanket-hold |
| TIC / hyperfibrinolysis | TXA + ratio MTP + TEG/ROTEM-guided cryo/plt/FFP | See Hemorrhagic Shock | Do not give TXA late (>3 h trauma) routinely |
ARDS ventilation by phenotype
Trauma and Critical Care
| Phenotype | TV / pressure | RR / I:E | PEEP / FiO2 / target |
|---|---|---|---|
| Default post-intubation | 6–8 mL/kg PBW | RR 16–20; I:E ~1:2 | PEEP 5–8; FiO2 1.0 then wean; SpO2 92–96% |
| ARDS | 6 mL/kg (4–8); Pplat <30 | RR 16–24 to pH ≥7.20 | PEEP/FiO2 table; prone if P/F <150 |
| Obstructive | 6–8 mL/kg; flow 60–80 L | RR 10–14; I:E 1:3–1:5 | PEEP 0–5; SpO2 88–92%; flow to zero |
| Metabolic acidosis | 6–8 mL/kg | RR 22–30 to match pre-RSI MV | Do not cut RR after RSI |
| Chronic retainer / high HCO3 | 6–8 mL/kg | RR to pH 7.35–7.40, not PaCO2 40 | SpO2 88–92%. Do not erase their HCO3 |
| Metabolic alkalosis, pH >7.45 | 6–8 mL/kg | Lower RR 10–14; allow PaCO2 up | Acetazolamide if volume overloaded |
| RV failure / massive PE | 6 mL/kg; avoid high Pplat | Avoid high RR / auto-PEEP | Modest PEEP; support BP first |
Bethesda Class
The Concise Surgery Review Manual
| Bethesda Class | Definition | CA Risk (% per SCORE) | Treatment |
|---|---|---|---|
| I | Non-diagnostic | 5-10 (17) | Repeat fine-needle aspiration |
| II | Benign | 0-3 (4) | Clinical f/u |
| III | AUS or FLUS Atypia of Undetermined Significance Follicular Lesion of Undetermined Significance | 10-30 (16) | Repeat fine-needle aspiration (vs RNA gene panel to assess need for lobectomy) |
| IV | Follicular Neoplasm | 25-40 (26) | Repeat fine-needle aspiration (vs RNA gene panel to assess need for lobectomy) |
| V | Suspicious | 50-75 (75) | Lobectomy |
| VI | Malignant | >97 (99) | Lobectomy vs Total |
CAH Type (most common to LC)
The Concise Surgery Review Manual
| CAH Type (most common to LC) | blood pressure ↑ before sex. 1 = ↑ Ø1 = ↓ | |
|---|---|---|
| CAH Type (most common to LC) | blood pressure | Virilization |
| 21 | ↓ | ↑ |
| 11 | ↑ | ↑ |
| 17 | ↑ | ↓ |
Cancer Genes
The Concise Surgery Review Manual
| CANCER GENES | ||
|---|---|---|
| Gene | Function | Cancers |
| ATM | Serine/threonine kinase DNA repair/apoptosis | Neuro/vasc, leukemia, lymphoma |
| BRCA1 | Transcription via RNA polymerase | Breast, ovary |
| BRCA2 | DNA repair (direct action/binding) | Breast, ovary, prostate, pancreas |
| CDH1 | Cell adhesion via cadherin | Stomach, breast |
| CHEK2 | Serine/threonine kinase DNA repair/apoptosis | Bladder, breast, colorectal cancer |
| p16 (FAMMM) | Tumor suppressor, slows progression from G1 to S phase | Breast |
| p53 (Li Fraumeni) | Regulates cell division | Adrenal, brain (GBM), breast, blood, lung, sarcoma |
| PALB2 | dsDNA repair | Breast, pancreas |
| PTEN (Cowden) | Phosphatase cell cycle regulation | Breast, endometrial, RCCa, thyroid |
| STK11 (Peutz Jeghers) | Serine/Threonine Kinase | Endometrial, GI, HCC, ovarian, pancreas |
Colon & Rectal Adenocarcinoma
The Concise Surgery Review Manual
| Colon & Rectal Adenocarcinoma | |||||
|---|---|---|---|---|---|
| TMN | Stages | Colon (no radiation therapy) | Rectal | ||
| Tis | CIS, into lamina propria | 0 | Tis | All colon cancer get segmental colectomy | Trans-anal resection |
| T1 | Into submucosa | I | T1-2 | All colon cancer get segmental colectomy | Trans-abdominal resection |
| T2 | Into muscularis propria | I | T1-2 | All colon cancer get segmental colectomy | Trans-abdominal resection |
| T3 | Through propria into pericolorectal tissues | IIA | T3 | Adjuvant: T3 Capecitabine or 5-FU + leucovorin >T3 FOLFOX or CAPEOX All for 6mns | If T3/4 or N1/2 or = Neoadjuvant radiation therapy + Capecitabine operating room Infusional 5-FU operating room FOLFOX operating room CapeOX + Resect |
| T4a | Visceral peritoneum | IIB | T4a | Adjuvant: T3 Capecitabine or 5-FU + leucovorin >T3 FOLFOX or CAPEOX All for 6mns | If T3/4 or N1/2 or = Neoadjuvant radiation therapy + Capecitabine operating room Infusional 5-FU operating room FOLFOX operating room CapeOX + Resect |
| T4b | Other organs | IIC | T4b | Adjuvant: T3 Capecitabine or 5-FU + leucovorin >T3 FOLFOX or CAPEOX All for 6mns | If T3/4 or N1/2 or = Neoadjuvant radiation therapy + Capecitabine operating room Infusional 5-FU operating room FOLFOX operating room CapeOX + Resect |
| N1a | 1 regional LN | IIIA | T1-2+N1; T1N2a | Adjuvant: T3 Capecitabine or 5-FU + leucovorin >T3 FOLFOX or CAPEOX All for 6mns | If T3/4 or N1/2 or = Neoadjuvant radiation therapy + Capecitabine operating room Infusional 5-FU operating room FOLFOX operating room CapeOX + Resect |
| N1b | 2-3 regional LNs | IIIB | T3-4a, N1; T2-3, N2a; T1-2+T2b | Adjuvant: T3 Capecitabine or 5-FU + leucovorin >T3 FOLFOX or CAPEOX All for 6mns | If T3/4 or N1/2 or = Neoadjuvant radiation therapy + Capecitabine operating room Infusional 5-FU operating room FOLFOX operating room CapeOX + Resect |
| N1c | Deposit in subserosal, mesentary, non-perioclolic tissue | IIIC | T4a, N2a; T3-4a, N2b; T4b+N1-2 | Adjuvant: T3 Capecitabine or 5-FU + leucovorin >T3 FOLFOX or CAPEOX All for 6mns | If T3/4 or N1/2 or = Neoadjuvant radiation therapy + Capecitabine operating room Infusional 5-FU operating room FOLFOX operating room CapeOX + Resect |
| N2a | 4-6 regional LN | IVA | AnyT/N, M1a | Neoadjuvant/ definitive chemotherapy | If T3/4 or N1/2 or = Neoadjuvant radiation therapy + Capecitabine operating room Infusional 5-FU operating room FOLFOX operating room CapeOX + Resect |
| N2b | >6 regional LN | IVB | Any T/N, M1b | Neoadjuvant/ definitive chemotherapy | If T3/4 or N1/2 or = Neoadjuvant radiation therapy + Capecitabine operating room Infusional 5-FU operating room FOLFOX operating room CapeOX + Resect |
| M1a | 1 organ | >2cm from dentate → LAR | |||
| M1b | >1 organ | <2cm from dentate → APR |
Di
The Concise Surgery Review Manual
| DI | Dehydration | SIADH | CSW | primary Polydispia | |
|---|---|---|---|---|---|
| UOP | ↑ | ↓ | ↓ | ↑ | ↑ |
| uOSM | ↓ | ↑ | ↑ | ↑ | ↓ |
| pVol | ↓ | ↓ | ↑ | ↓ | ↑ |
| pOSM | ↑ | ↑ | ↓ | ↓ | ↓ |
| pNa+ | ↑/normal | ↑/normal | ↓ | ↓ | ↓/normal |
Disease
The Concise Surgery Review Manual
| Disease | Diagnosis | Treatment | |
|---|---|---|---|
| DES | Early contractions on ≥20% of swallows, ↓distal latency time (<4.5s), 3°, non-peristaltic, normal LES | 1st CCBs, 2nd nitrates/Botox Consider POEM (vs long Heller) | |
| Nutcracker | High-amplitude (>180), normal LES | 1st CCBs, 2nd nitrates/Botox | |
| Scleroderma | Aperistaltic, low LES mmHg | PPI, Reglan, partial wrap (if GERD is main problem), total esophagectomy (last resort) | |
| Achalasia (absent peristalsis, Integrated Relax Pressure at LES >15) | I | No change in esophageal mmHg, 100% failed peristalsis, distal esophageal contraction, < 100 mmHg, No pressurization | Heller myotomy (vs dilation). |
| Achalasia (absent peristalsis, Integrated Relax Pressure at LES >15) | II | Diffuse esophageal mmHg ≥20% of swallowing, 100% failed peristalsis, Panesophageal pressurization | Heller myotomy (vs dilation). |
| Achalasia (absent peristalsis, Integrated Relax Pressure at LES >15) | III | No normal peristalsis, but spastic contractions & DCI >450 on ≥20% of swallows, Premature | POEM |
Dysrhythmia treatment
Trauma and Critical Care
| Rhythm | 1st line | 2nd / 3rd | Pearls |
|---|---|---|---|
| AF with RVR, stable | Rate: metoprolol 5 mg IV q5 ×3 or esmolol; dilt 0.25 mg/kg then 5–15 mg/h if EF ok | Amio 150 mg then 1 mg/min ×6 h → 0.5 mg/min; digoxin if low EF + rate | Anticoag if >48 h or unknown before elective DCCV; TEE vs 3-wk rule |
| Aflutter | Same rate control; easier DCCV (50 J) | Ablation destination therapy | 1:1 conduction if class Ic without AV nodal agent |
| SVT (AVNRT/AVRT) | Vagal; adenosine 6/12 | Beta-blocker, CCB, ablation | WPW + AF: avoid AV nodal agents; procainamide / shock |
| Monomorphic VT stable | Amio 150 mg / lido 1–1.5 mg/kg | Procainamide 10–17 mg/kg (avoid if HF/QT) | Revasc if ischemic; check Mg, K>4, Mg>2 |
| TdP / polymorphic VT + long QT | Unsync shock if unstable; Mg 2 g IV regardless of level | Overdrive pacing; isoproterenol if pause-dependent | Stop QT drugs; replete K |
| High-grade AV block | TCP / atropine if nodal | Dopamine/epi bridge to PPM | Mobitz II and 3rd-degree = pacemaker territory |
Empiric antibiotics by source
Trauma and Critical Care
| Source / bugs | 1st line | 2nd / true β-lactam allergy |
|---|---|---|
| Dog — strep, staph, Pasteurella, Capnocytophaga, oral anaerobes | Amox-clav 875/125 PO BID. IV: amp-sulbactam 3 g q6h (pip-tazo if sick). | Moxifloxacin 400 mg daily, OR clinda 300–450 TID + TMP-SMX DS BID (AAST), OR doxy 100 BID + metro 500 TID. Do not use cephalexin, cefazolin, or clinda monotherapy (misses Pasteurella). |
| Cat — Pasteurella (~90%), strep, staph, anaerobes. Punctures infect 30–50%. | Same as dog. Prophylaxis for essentially all cat bites, especially the hand. | Doxy 100 BID (covers Pasteurella) ± metro. Moxifloxacin if severe allergy. Rapid cellulitis in hours is Pasteurella until proven otherwise. |
| Human — viridans strep, Eikenella, oral anaerobes, staph. Fight bite = MCP joint until disproven. | Amox-clav PO or amp-sulbactam IV. Face: irrigate and close; still cover. | Moxifloxacin 400 daily (covers Eikenella). Clinda + TMP-SMX is AAST’s allergy pair. Do not use clinda, metro, 1st-gen ceph, or macrolide monotherapy (Eikenella gap). |
| Feral hog / pig / livestock (Texas ranch) | Treat as a polymicrobial bite: amox-clav or Unasyn. Add tetanus. Consider rabies if feral and unobserved. | Moxifloxacin, or clinda + TMP-SMX. Deep punctures of the hand go to the OR. |
| Asplenic / liver disease + dog saliva | Capnocytophagacanimorsus can kill. Unasyn or pip-tazo or a carbapenem. Do not delay. | Carbapenem or cipro + clinda if truly no β-lactam. |
FENa
The Concise Surgery Review Manual
| FENa | FEUrea | uNa+ | OSM | BUN/Cr | |
|---|---|---|---|---|---|
| Pre | < 1% | < 35% | < 10 | > 500 | > 20 |
| Renal | > 2% | 50-65% | > 20 | < 350 | < 15 |
| posterior | > 4% | - | > 40 | < 350 | > 15 |
Gallbladder Cancer
The Concise Surgery Review Manual
| Gallbladder Cancer | |||
|---|---|---|---|
| tumor-node-metastasis | Depth | St | treatment |
| T1a | Lamina propria | 1A | laparoscopic chole (~100% cure) |
| T1b | Muscularis propria | 1A | laparoscopic chole + wedge IVb+V (2cm margins) |
| T2 | Perimuscular tissue | 1B | laparoscopic chole, formal IVb+V, portal LNDx (≥3 LNs), common bile duct resection (send frozen) w/H-J, adj gemcitabine + cisplatin |
| T3 | Serosal/liver/ adj organ | IIA | laparoscopic chole, formal IVb+V, portal LNDx (≥3 LNs), common bile duct resection (send frozen) w/H-J, adj gemcitabine + cisplatin |
| N1 | IIB | Palliative (gemcitabine + cisplatin) | |
| T4 | Main portal vein, hepatic artery, 2+ organs | III | Palliative (gemcitabine + cisplatin) |
| M1 | IV | Palliative (gemcitabine + cisplatin) |
Gi Losses
The Concise Surgery Review Manual
| GI LOSSES | |||||
|---|---|---|---|---|---|
| L/d | Na+ | Cl- | K+ | HCO3- | |
| Saliva | 1.5 | 50 | 40 | 20 | 30 |
| Gastric | 2 | 100 | 140 | 10 | - |
| Small Bowel | 3 | 80-150 | 60-115 | 5 | D- 10 I- 30-50 |
| Bile | 0.5-1 | 140 | 100 | 5 | 25 |
| Pancreas | 1.5-3 | 140 | 60 | 5 | 80-115 |
| Colon | varies | 120 | 90 | 25 | 45 |
ICU drug doses
Trauma and Critical Care
| Line | Drug | Dose | Use / avoid |
|---|---|---|---|
| 1st inotrope | Dobutamine | 2–20 mcg/kg/min | Low CI, high SVR; arrhythmia |
| 1st inodilator | Milrinone | 0.125–0.75 mcg/kg/min | RV / on BB; accumulates in AKI |
| 1st pressor | Norepinephrine | 0.01–0.5+ mcg/kg/min | Preferred if SBP low |
| 2nd | Epinephrine | 0.01–0.1 mcg/kg/min | Profound CS; lactate up |
| Rescue | Ang II / vasopressin | 5–40 ng/kg/min / 0.03 U/min | Vasoplegic mixed shock |
Laceration closure timing
Trauma and Critical Care
| Wound | Closure | Notes |
|---|---|---|
| Face / scalp, including selected bites <24 h after thorough irrigation | Primary closure preferred | Rich blood supply; better cosmetic result. Still cover with bite antibiotics. Facial Trauma protocol: complex/high-risk operative lacerations get cefazolin 2 g ×1 preop, ≤24 h — that does not replace irrigation or bite coverage. |
| Hand, puncture (especially cat), clenched-fist fight bite | Do not close. Delayed or secondary. | Closed space / tendon sheath. Hand surgery if tenosynovitis or MCP joint violation. |
| Dog laceration, low-risk, <8–12 h, not hand/foot | May close primarily after irrigation | IDSA: closure after irrigation is reasonable if not high-risk. Leave a drain if deep. |
| Human bite (not face), farm/soil, salt or fresh water | Delayed primary after debridement | High bioburden. Close later when clean. |
| Open fracture (any contamination) | Ortho washout; do not primarily close type III | Open Fracture protocol. Coverage of type III is Ortho’s call after serial debridement. |
Levels Of Sedation & Their Effects
The Concise Surgery Review Manual
| LEVELS OF SEDATION & THEIR EFFECTS | ||||
|---|---|---|---|---|
| Minute | Mod/Conscious | Deep | General Anesthesia | |
| Airway | OK | OK | Probably OK | Not OK |
| Blood pressure | NML | Typically NML | Typically NML | ↓ |
| Response | NML | Purposeful | Purposeful to repeated / noxious stimuli | None |
| Ventilation | NML | OK | Probably OK | Not OK |
Multimodal analgesia ladder
Trauma and Critical Care
| Line | Agent | Dose / notes | Avoid / caution |
|---|---|---|---|
| 1st | Acetaminophen | 1 g IV/PO q6–8h (max 3–4 g/d; 2 g if liver failure) | Acute liver failure |
| 1st | Ketamine | 0.1–0.3 mg/kg/h or 0.1–0.3 mg/kg IV | Uncontrolled HTN, psychosis |
| 1st | Gabapentinoid | Gabapentin 100–300 mg TID (renal dose) | Sedation, edema |
| 1st/2nd | Ketorolac | 15 mg IV q6h × ≤5 d | AKI, bleed, anastomosis, PUD, CABG |
| 2nd | Opioid IV | Fentanyl 25–50 mcg / 25–200 mcg/h; hydro 0.2–1 mg | Rigidity with push; accumulation |
| 2nd/3rd | Lidocaine IV | 1 mg/kg then 1–2 mg/kg/h | Heart block, neurotoxicity |
Nec
The Concise Surgery Review Manual
| NEC | ||||||
|---|---|---|---|---|---|---|
| Stage | Clinical | Exam/Lab | Radiographic | Medical treatment | Surgical treatment | |
| I | A | Suspected NEC, ↑/↓ temp, ↓heart rate, emesis | Distension, fecal occult blood test+ | ± Dilation | antibiotics (Vanc + gent / ceftriaxone), nil per os, decompression, intravenous fluid resus, parenteral nutrition AND q6-8h exams, CBC, & 2-view x-ray. | / |
| I | B | Suspected, SAA | Grossly bloody stools | SAA | antibiotics (Vanc + gent / ceftriaxone), nil per os, decompression, intravenous fluid resus, parenteral nutrition AND q6-8h exams, CBC, & 2-view x-ray. | / |
| II | A | Definite NEC, SAA, ± TTP | SAA | Dilation, pneumatosis | antibiotics (Vanc + gent / ceftriaxone), nil per os, decompression, intravenous fluid resus, parenteral nutrition AND q6-8h exams, CBC, & 2-view x-ray. | / |
| II | B | Definite, SAA, ± cellulitis | Metabolic acidosis, ↓platelets | SAA + ascites | antibiotics (Vanc + gent / ceftriaxone), nil per os, decompression, intravenous fluid resus, parenteral nutrition AND q6-8h exams, CBC, & 2-view x-ray. | Relative indications failure to progress, compartment synd, abd wall erythema, portal venous gas, fixed loops. primary drain for VLBW infants. Resect dead bowel, divert if focal/2nd look if multifocal. |
| III | A | Advanced NEC, SAA, ↓blood pressure | Apnea, ↓WBC, disseminated intravascular coagulation | SAA | antibiotics (Vanc + gent / ceftriaxone), nil per os, decompression, intravenous fluid resus, parenteral nutrition AND q6-8h exams, CBC, & 2-view x-ray. | Relative indications failure to progress, compartment synd, abd wall erythema, portal venous gas, fixed loops. primary drain for VLBW infants. Resect dead bowel, divert if focal/2nd look if multifocal. |
| III | B | Advanced, perforated | Peritonitis | Pneumo-peritoneum | antibiotics (Vanc + gent / ceftriaxone), nil per os, decompression, intravenous fluid resus, parenteral nutrition AND q6-8h exams, CBC, & 2-view x-ray. | Relative indications failure to progress, compartment synd, abd wall erythema, portal venous gas, fixed loops. primary drain for VLBW infants. Resect dead bowel, divert if focal/2nd look if multifocal. |
Noninvasive ventilation
Trauma and Critical Care
| Modality | Physiology | Best indications | Avoid / fail cues |
|---|---|---|---|
| HFNC | Flow up to 40–60 L; dead-space washout, modest PEEP, heated humidify | Hypoxemic RF (type 1), post-extubation high risk, palliation | Hypercapnic pump failure as sole therapy; delayed intubation (ROX <3–5 trajectory) |
| CPAP | Constant PEEP | Cardiogenic pulmonary edema, OSA, atelectasis | High aspiration risk, vomiting |
| BiPAP (IPAP/EPAP) | PS + PEEP; unloads CO2 | COPD/asthma exacerbation, OHS, cardiogenic edema, selected neuromuscular | Unprotected airway, facial trauma, untreated pneumothorax, active vomit, GCS low |
| Helmet NIV | Better tolerance, less leak | Hypoxemic RF in experienced centers (COVID-era data) | Logistics, claustrophobia, CO2 if flow low |
Open-fracture / contamination antibiotics
Trauma and Critical Care
| Contamination | Bugs | 1st line | 2nd / allergy |
|---|---|---|---|
| Salt / brackish / Gulf / bay / fish, shrimp, catfish, or stingray spine | Vibrio vulnificus, other Vibrio, GNR | open fx: ceftriaxone 2 g q24h + metro 500 q8h + doxycycline 100 mg IV/PO q12h × 24 h (max 72 h if Ortho documents severe contamination). Soft tissue (AAST/IDSA): doxy + 3rd-gen ceph (ctx or ceftazidime) or a FQ × 3–5 d prophylaxis. Cirrhosis / hemochromatosis: this is an emergency — debride necrotizing infection now and add doxy. | Levo 500 + metro + doxy. Do not treat a Gulf cut with cephalexin. |
| Fresh water / river / lake / irrigation / stock tank | Aeromonas, Pseudomonas, Plesiomonas | open fx: pip-tazo 4.5 g q6h (replaces ctx+metro) × 24 h. Soft tissue (AAST): cipro or levo or 3rd/4th-gen ceph × 3–5 d. | Levo 500 + metro. Do not treat a lake or stock-tank cut with cephalexin. |
| Farm / soil / manure / fecal / ranch | Clostridium, mixed GNR, anaerobes | open fx: ceftriaxone 2 g q24h + metro 500 q8h × 24 h (Ortho may extend to 72 h if severely contaminated). Soft tissue (AAST 2024): 3–5 d. AAST/EAST add high-dose penicillin for Clostridium; Open Fracture protocol explicitly does not add high-dose PCN for farm injuries — follow when bone is open. | Levo + metro. Debridement beats a third antibiotic. |
| Sewage / standing ditch water | Polymicrobial GNR + anaerobes ± Aeromonas | Pip-tazo or ctx + metro. Add doxy if brackish mix. | Levo + metro. |
| Open fx without special contamination | Skin flora | Type I–II: cefazolin 2 g q8h (3 g if ≥120 kg) × 24 h. Type III: ceftriaxone 2 g q24h × 24 h, then only with each debridement. | Clinda 900 q8h (I–II) or levo 500 (III). Documented penicillin / pip-tazo / ceftriaxone allergy is not a cefazolin allergy — cefazolin remains 1st line. |
Pre-Op Steroid Recs
The Concise Surgery Review Manual
| PRE-OP STEROID RECS | ||
|---|---|---|
| Pre-op Prednisone Equivalent | Type of surgery | Recs (AM / Induction) |
| < 10 mg/d (or >3mn off steroids) | normal response | normal AM dose |
| 10-59 mg/d | Minor | AM dose / 25mg hydrocortisone |
| 10-59 mg/d | Mod | AM dose / 50mg hydrocortisone then 1d taper |
| 10-59 mg/d | Major | AM dose / 100mg hydrocortisone then 1-2d taper |
| ≥ 60 mg/d | Adrenal Suppression | 80mg hydrocortisone Q8H then taper |
Pressor and inotrope roles
Trauma and Critical Care
| Line | Agent | Dose | Role |
|---|---|---|---|
| 1st | Norepinephrine | 0.01–0.5+ mcg/kg/min | First-line. Peripheral OK short-term. |
| 2nd add-on | Vasopressin | 0.03 U/min fixed | Add at NE ~0.25–0.5 |
| 2nd/3rd | Epinephrine | 0.01–0.1 mcg/kg/min | Low CI or refractory |
| Rescue | Angiotensin II | 5–40 ng/kg/min | ATHOS-3; thrombosis risk |
| Inotrope | Dobutamine | 2–20 mcg/kg/min | Persistent hypoperfusion + low CI |
Quick vasoactive pocket
Trauma and Critical Care
| Drug | Example mix | Start | Usual range |
|---|---|---|---|
| Norepinephrine | 8 mg / 250 mL D5W (32 mcg/mL) | 0.05 mcg/kg/min | 0.01–0.5+ |
| Vasopressin | 20 U / 100 mL NS | 0.03 U/min | 0.01–0.03 |
| Epinephrine | 4 mg / 250 mL | 0.02–0.05 mcg/kg/min | 0.01–0.1+ |
| Phenylephrine | 40 mg / 250 mL | 0.5 mcg/kg/min | 0.1–2 |
| Dobutamine | 250 mg / 250 mL | 2.5–5 mcg/kg/min | 2–20 |
| Milrinone | 20 mg / 100 mL | 0.25 mcg/kg/min (no load if unstable) | 0.125–0.75 |
| Nicardipine | 20–40 mg / 200 mL | 5 mg/h | 5–15 |
| Regular insulin DKA | 100 U / 100 mL NS | 0.1 U/kg/h | Titrate to close the gap |
Rifle / Akin
The Concise Surgery Review Manual
| RIFLE / AKIN | Cr/GFR | UOP |
|---|---|---|
| Risk / AKIN I | ↑ Cr 1.5x ↓ GFR > 25% | < 0.5mL/kg/hr x 6 hours |
| Injury / AKIN II | ↑ Cr 2x ↓ GFR > 50% | < 0.5mL/kg/hr x 12 hours |
| Failure / AKIN III | Cr 4mg/dL ↓ GFR > 75% | < 0.3mL/kg/hr x 24 hours or anuria x 12hours |
| Loss | acute kidney injury > 4 weeks | |
| ESRD | acute kidney injury > 3 months |
RSI and sedation drugs
Trauma and Critical Care
| Line | Drug | Dose | Notes / CI |
|---|---|---|---|
| 1st | Propofol | 5–50 mcg/kg/min | PRIS if high dose >48 h + pressors. Hypotension. |
| 1st | Dexmedetomidine | 0.2–1.4 mcg/kg/h | Brady/hypotension. Not deep sedation alone. |
| 2nd | Midazolam / lorazepam | 1–5 mg/h / 1–2 mg IV | Delirium; PG acidosis with lorazepam drip. |
| Adjunct | Ketamine | 0.1–0.5 mg/kg/h | Preserves drive; secretions. |
| Rescue | Cisatracurium | 0.15 mg/kg then 1–3 mcg/kg/min | Must be deeply sedated first. TOF. |
Source-control empiric therapy
Trauma and Critical Care
| Source | Typical empiric | Severe β-lactam allergy | Source control |
|---|---|---|---|
| Pneumonia | See Pneumonia | Aztreonam or levo + MRSA agent | Drain empyema |
| Intra-abdominal | Pip-tazo or cefepime + metro | Cipro/aztreonam + metro + vanc | OR / IR |
| cUTI / pyelo | Ceftriaxone; pip-tazo or carbapenem if septic/MDRO | Aztreonam or cipro | Decompress obstruction |
| NSTI | Vanc/linezolid + pip-tazo/carbapenem + clinda | Linezolid + aztreonam + metro + clinda | Immediate OR |
| CLABSI | Vanc + cefepime (± candin if shock + risk) | Vanc + aztreonam | Pull the line if S. aureus/Candida/Pseudo/shock |
| Meningitis | Vanc + ctx 2 g q12 ± amp | Vanc + moxi ± TMP-SMX | CT then LP if safe |
| Neutropenic | Cefepime or pip-tazo or meropenem ± vanc | Aztreonam + vanc | Remove devices |
| Biliary | Pip-tazo or ctx + metro | Cipro + metro | ERCP |
| SSTI non-nec | Vanc or cefazolin if MSSA likely | Linezolid / daptomycin | I&D |
| Unknown shock | Pip-tazo or meropenem + vanc | Aztreonam + metro + vanc | Exam + CT + lines + urine + skin |
T-staging by depth — esophagus, stomach, colon, rectum, gallbladder
Oral Board Flashcards
| Stage | Esophagus | Stomach | Colon | Rectum | Gallbladder |
|---|---|---|---|---|---|
| T1a | Lamina propria Muscularis mucosa | Lamina propria Muscularis mucosa | Submucosa | Submucosa | Lamina propria |
| T1b | Submucosa | Submucosa | Muscularis propria | ||
| T2 | Muscularis propria | Muscularis propria | Muscularis propria | Muscularis propria | Perimuscular |
| T3 | Adventitia | Adventitia | Adventitia | Adventitia | Serosa/Adventitia |
| T4 | Surrounding tissue | Surrounding tissue | Visceral peritoneum | Surrounding tissue | Portal vein, Hepatic artery, or 2+ organs |
T-staging by size — breast, anal canal, perianal, lung
Oral Board Flashcards
| Stage | Breast | Anal Canal SCCa | Perianal/Margin | Lung |
|---|---|---|---|---|
| T1 | < 2cm | < 2cm | < 2cm | ≤ 3cm |
| T2 | > 2cm – 5cm | > 2cm – 5cm | > 2cm – 5cm | > 3cm – 5cm |
| T3 | > 5cm | > 5cm | > 5cm | > 5cm – 7cm |
| T4 | Skin Chest Wall | Surrounding tissue | Surrounding tissue | > 7cm |
| Inflammatory |
Type
The Concise Surgery Review Manual
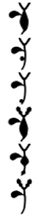 | Type | Choledochal Cyst Description | Treatment |
|---|---|---|---|
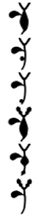 | I | Cylindric or fusiform common bile duct dilation | most common, 77-87% / resect w/Roux-en-Y HJ |
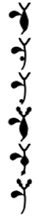 | II | Supraduodenal common bile duct diverticulum | Simple cyst excision |
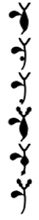 | III | Intraduodenal common bile duct diverticulum (asso with SOD) | Choledochocele / sphincterotomy vs endoscopic resection |
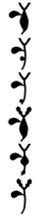 | IVa | Intra & extra hepatic dilations | Partial hepatectomy + wide hilar Roux-en-Y HJ. May need transplant. |
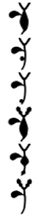 | IVb | Extra hepatic dilations | Complete resection + Roux-en-Y HJ |
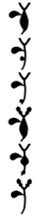 | V | Intra hepatic dilations | Caroli disease (disease + renal cyst = Caroli synd) / supportive vs transplant |
Ventilator modes
Trauma and Critical Care
| Mode | What it does | Use when | How / pitfalls |
|---|---|---|---|
| VC-CMV (AC/VC) | Set TV; pressure varies | Most ICU starts; guaranteed TV | Watch Pplat. Flow starvation if flow low |
| PC-CMV (AC/PC) | Set Pinsp; TV varies | Limit pressure, variable Crs | TV drifts — watch MV |
| PRVC / VC+ | Targets TV with variable P | Convenience hybrid | May under-support strong effort |
| PS / SPONT | Patient-triggered PS + PEEP | Wean, intact drive | PS 5–8; high PS hides weakness |
| SIMV ± PS | Mandatory + spontaneous | Transitional (declining use) | Often increases work |
| APRV / BiLevel | High P, high T, brief release | Recruitable ARDS, salvage | Tlow so release flow ~75% peak |
Educational aid only. Verify every dose, indication, and guideline against current institutional protocol. This is not a substitute for clinical judgment.